

Ovarian Cysts

Ovarian Cyst is a sac of fluid or tissue formed within the ovary
It is normal to have an ovarian cyst each month before menstruation.
This functinal ovarian cyst is called the Corpus Luteal Cyst. It will go away after menstruation.
Click here for menstruation cyst diagram.
What are the Common Types of Ovarian Cysts?
“Water Cyst” or Functional ovarian cysts are the most common cyst in the reproductive age. They contain only fluid or blood and usually resolve in a month or two. They are usually less than 5cm although rarely they may be as large as 8cm.
“Blood Cyst” or Endometriomas (or chocolate cysts) are formed by Endometriosis where the womb lining is found outside the uterus leading to monthly bleeding in the pelvis. This sometimes forms blood cysts within the ovary and leads to painful menstruation or pelvic pain.
“Tissue Cyst” or Dermoid cyst (or benign mature cystic teratomas) usually contains oil and hair. Dermoid Cyst form because the ovary has cells with the potential to develop into any type of tissue. Hence, these cysts can also contain skin, fat, bone and cartilage. Dermoid cyst can happen in both ovaries in 10% of the time.
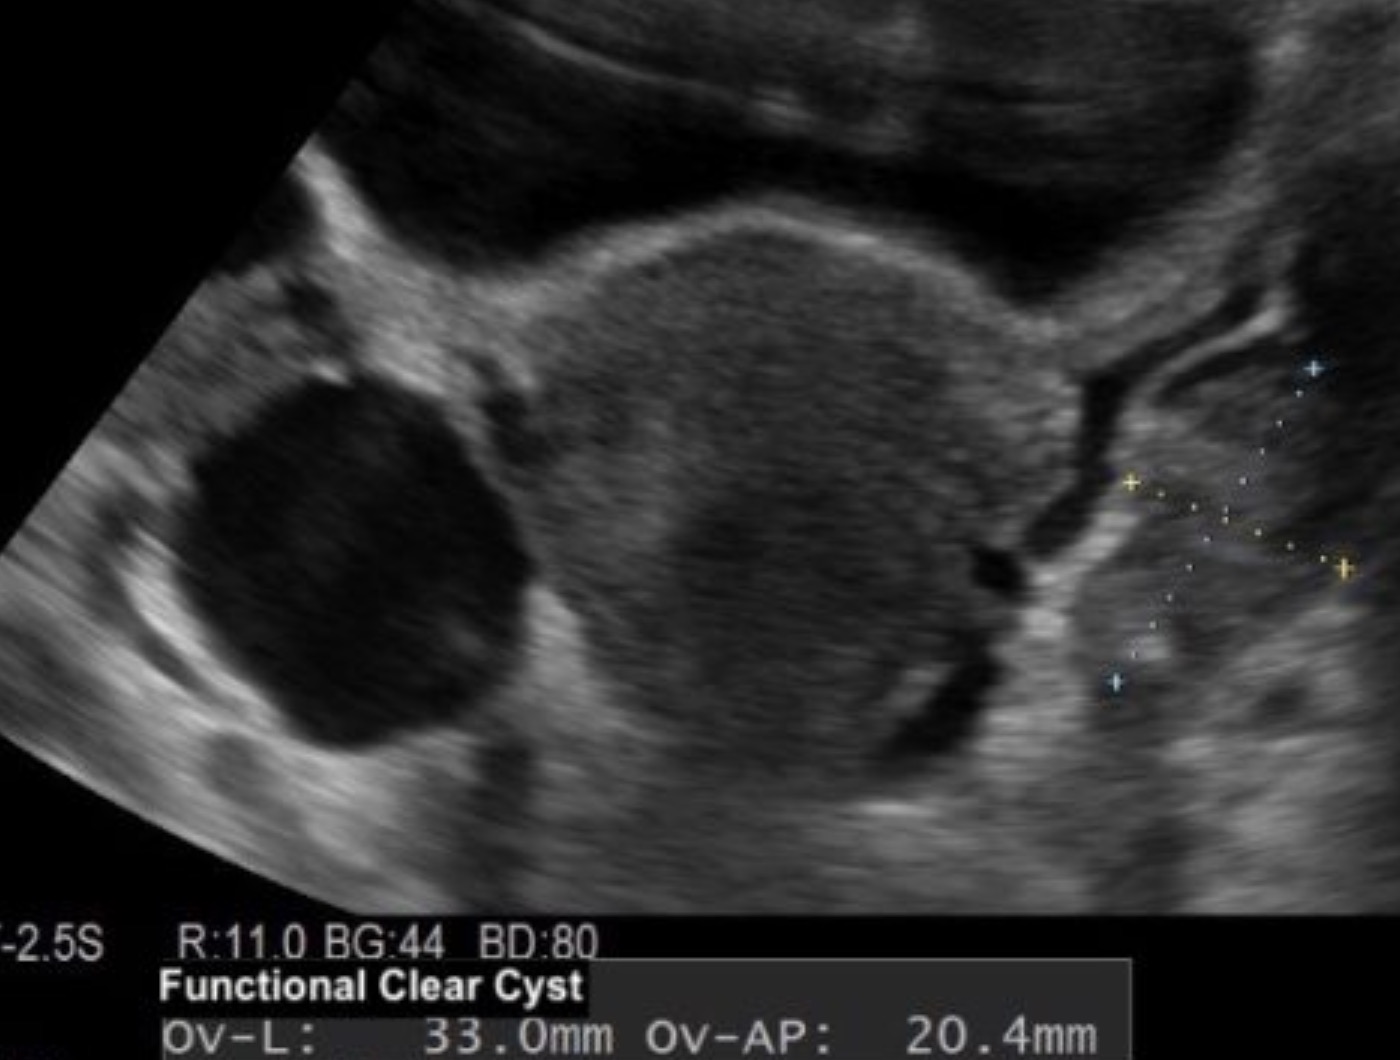
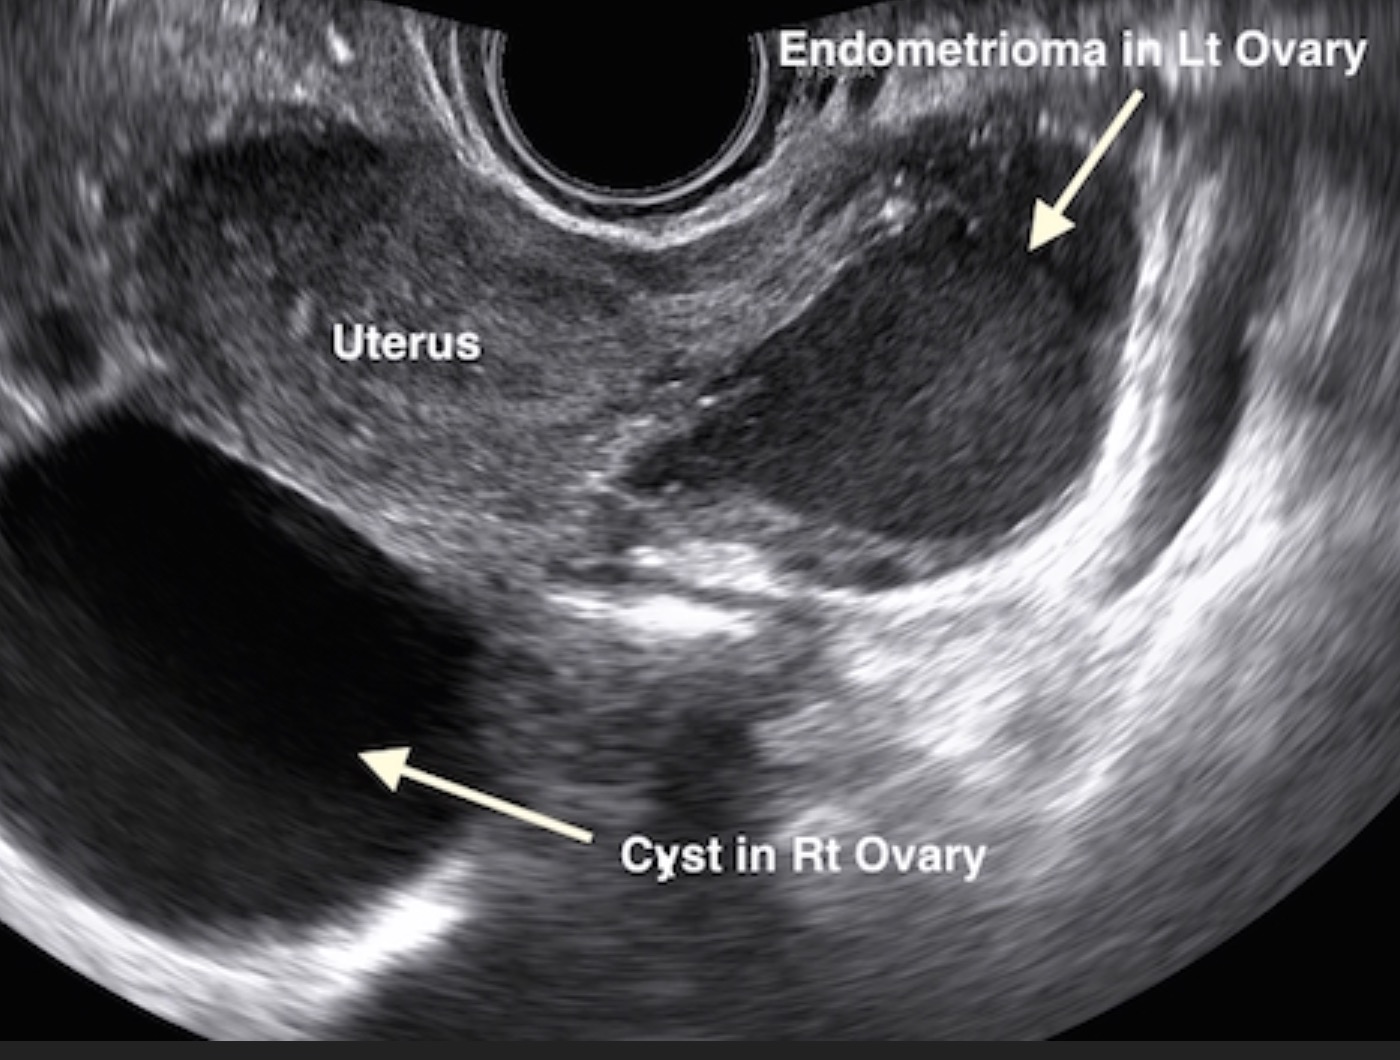
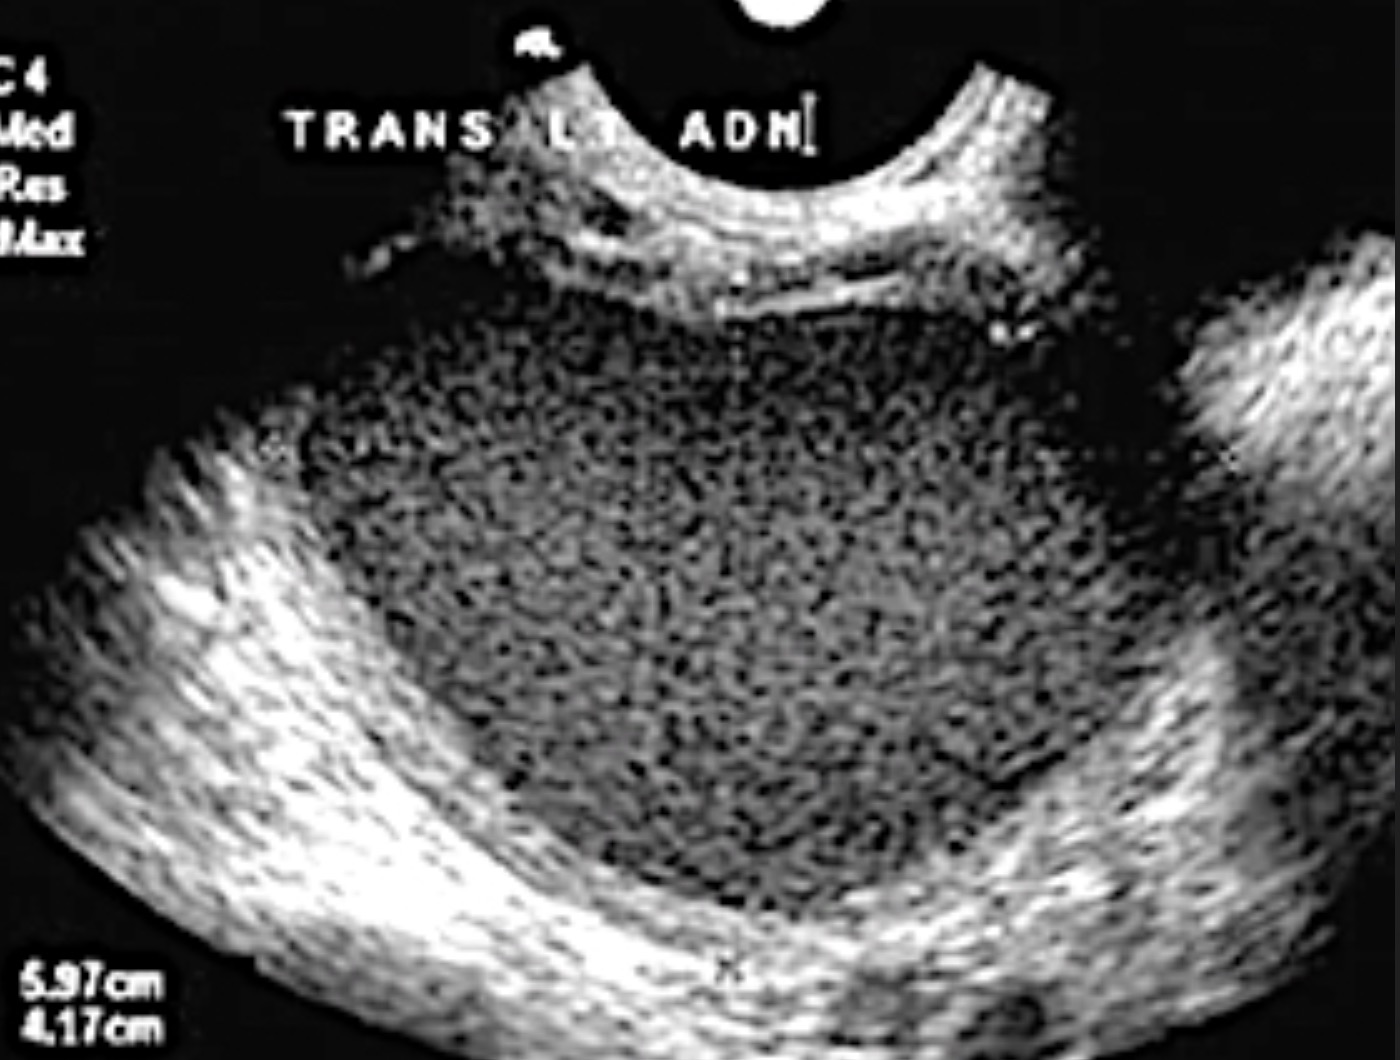
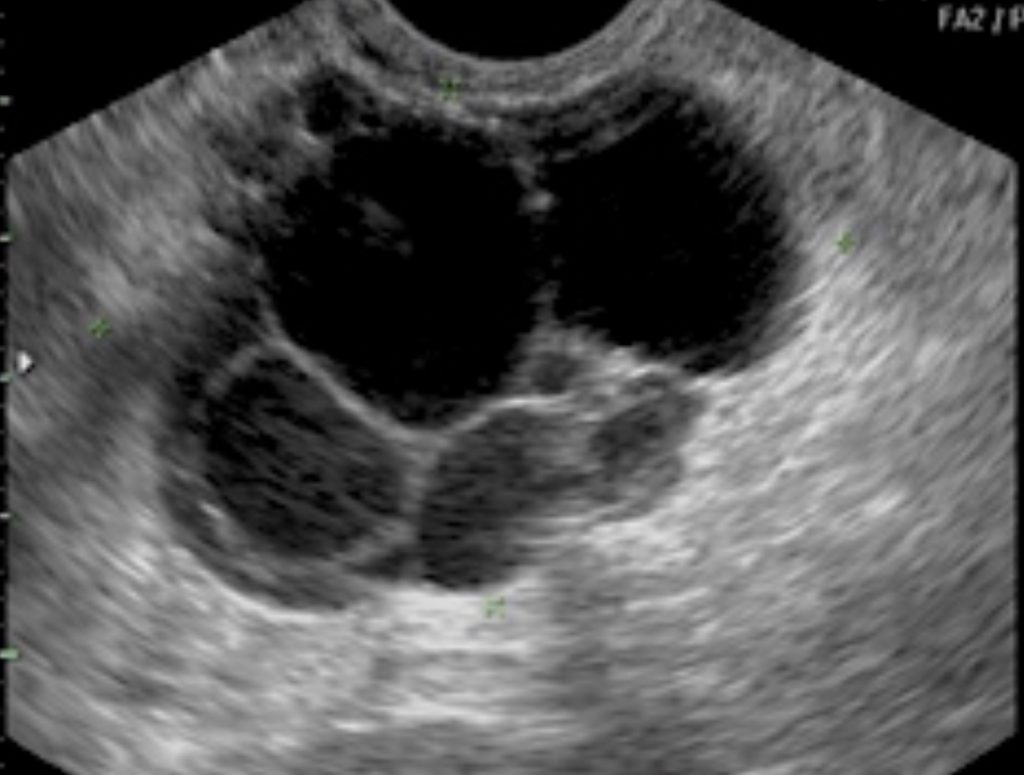
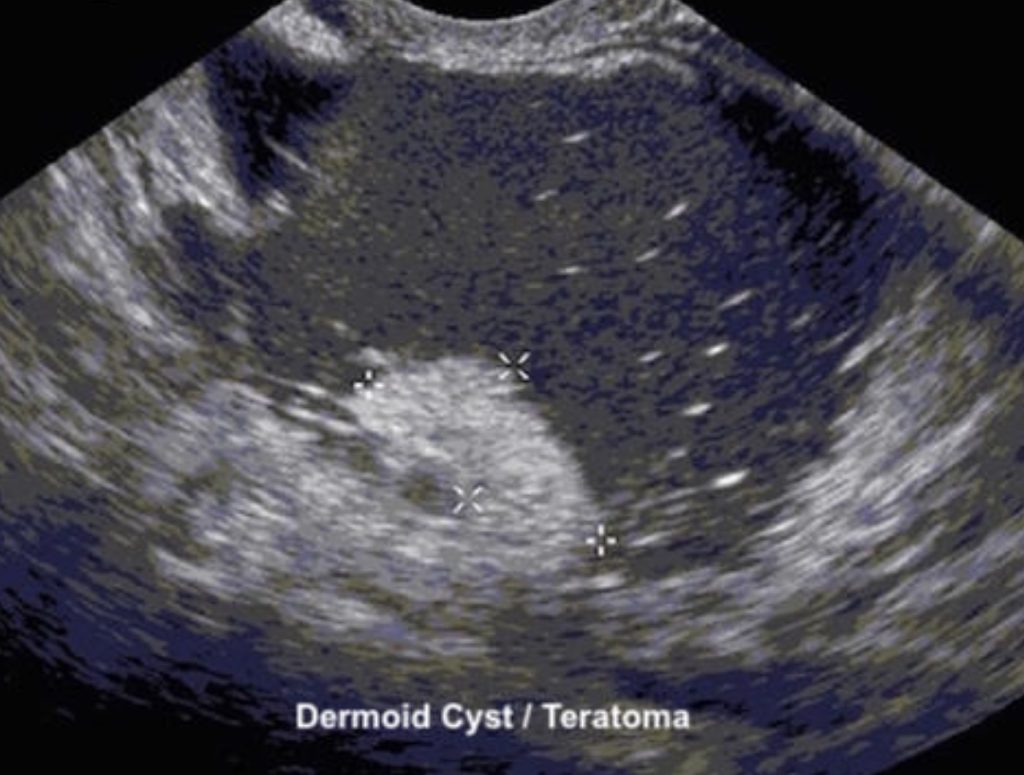
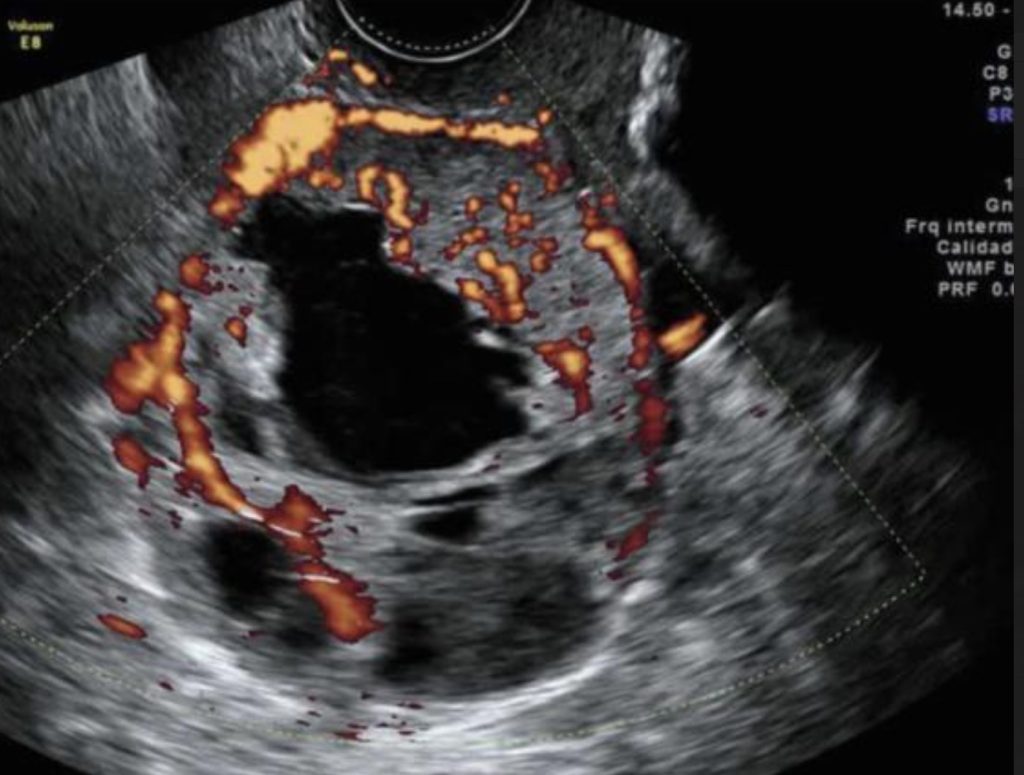
Ovary Cyst Size and Volume

What are the Symptoms of Ovarian Cysts?
Most ovarian cysts cause no symptoms because they are small and non-cancerous.
Some ovarian cysts may cause :-
❖ Pain or discomfort in the lower abdomen.
❖ Irregular menstruation if the cyst affects ovarian hormonal function.
❖ Urinary symptoms from pressure of a large cyst.
❖ Bloatedness and abdominal swelling.
❖ Torsion where the ovary is twisted, causing loss of blood flow to the ovary and severe pain.
❖ Leakage of cyst content, causing severe pain and bowel disturbances.


Do all ovarian cysts need treatment?
No, cysts with the following features may not need treatment.
❖ Cysts of < 4cm and not growing.
❖ Small cysts with no symptoms.
❖ Cyst with no unusual features.
These cysts can be monitored with 4-6 monthly ultrasounds.
A 2-year study of cyst treatment showed 15% of cysts resolved, 58% remained unchanged and 1-4% caused symptoms or problems.
In this study, only 8/2410 (0.3%) women were found to have cancer in their cysts.

What is the risk of ovarian cancer?
❖ The lifetime risk of ovarian cancer in the general population is 1.3%.
❖ The risk is slightly increased with some ovarian cysts to 1.7 – 1.9%.
❖ The risk of cancer is increased with a positive family history of
. – 2 or more 1st degree relative with ovarian cancer
. – 1 relative with ovarian cancer and 1-2 relatives with breast cancer
. – 2-3 relatives with ovarian, endometrium, bowel, stomach, urinary tract cancer
❖ The risk is lowered with pregnancy, breastfeeding, taking oral contraceptive pill or fallopian tube removal.

CA125 CANNOT be used to Diagnose Ovarian Cancer
❖ CA125 can be raised in many normal conditions. It can also be normal in early ovarian cancer.
. It is not accurate for diagnosis of ovarian cancer.
❖ The Risk of Malignancy Index (RMI) uses CA125 and clinical features to assess the chance of ovarian cancer.
. It also cannot be used to diagnose ovarian cancer.
❖ The RMI Score is used to plan the detail treatment of the ovarian cyst.

Does Ovary Cyst Become a Cancer?
How often should a ovarian cyst be scanned?
Professor Horiuchi reviewed the clinical charts of 543 women with ovary cancer.
35 women with ovary cancer had a pelvic ultrasound done within 12 months of surgery.
19/35 (54%) women had been follow up for benign appearing cysts with ultrasound between 2-12 months.
16/35 (46%) women had normal ultrasound findings 12 months prior.
The finding supports the two pathways of ovary cancer development; cyst becoming cancer and cancer forming from a normal ovary.

When is Surgery needed to remove ovarian cysts?
Surgery is needed when :-
❖ Ovarian cyst is large (>4cm) and growing.
❖ Ovarian cyst cause pain and severe symptoms.
❖ Ovarian cyst leads to pregnancy problems.
❖ A definitive diagnosis of the ovarian cyst is required.
Surgery for Ovarian Cyst
It is now common practice to remove ovarian cyst by Laparoscopic Keyhole Surgery, called Laparoscopic Ovarian Cystectomy.
The Conventional Laparoscopy Ovarian Cystectomy requires 3-4 cuts of 0.5-1.0 cm each.

In selected cases, Single Incision Laparoscopy can be done to removed the cyst with Just One Cut.
Single Incision Laparoscopic Ovarian Cystectomy results in fewer abdominal cuts, faster recovery and almost a scarless results.
Dr Anthony Siow carries out more than 90% of his surgery by Single Incision Laparoscopy

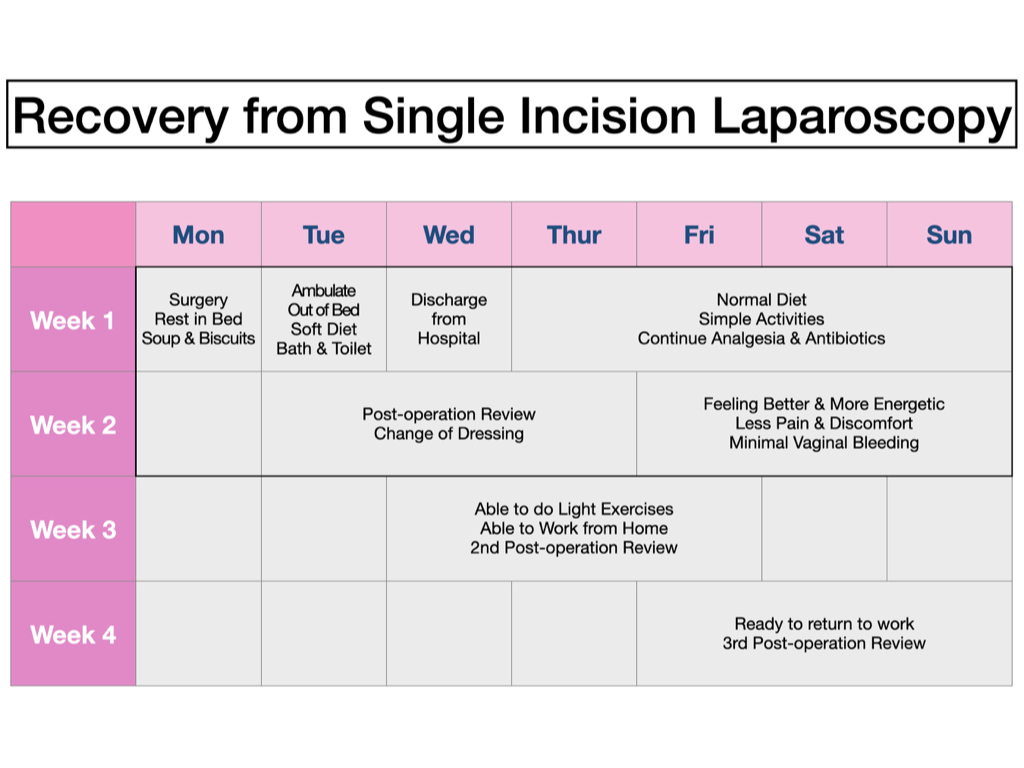
Almost all patients recover from surgery by Anthony Siow as follows:-
Day1 – is the surgery day. You will be resting in bed and can take some clear fluids. As you will not be mobile, a small urine tube is placed to help you pee.
Day2 – is 12-24hr after surgery. Most patients will have a marked reduction in pain. The urine tube will be removed and you should be able to walk around. You can start normal diet and take a shower.
Day3 – is when most patient feel almost recovered from surgery and are generally well enough to go home.
Day4-10 – is the first week after surgery at home. Pain and discomfort from surgery starts to disappear. Most patients are well enough to go outdoors for half the day. Some do not need anymore pain medication.
Week 2 after surgery is the usual time for postop review. Many patients feel normal and fine enough to go without pain medication. At the review, details of the surgery and biopsy results will be discussed. The surgical incision will be checked and the dressing changed.
Week 3 after surgery is the time most patient bounce back to normal. Some are able to start light exercises and gym training. Some can work from home if needed. You can start driving this week.
Hospitalisation leave of 4 weeks is usually given. A final postop review is done to ensure recovery is complete. Where needed, the hospitalization leave can be extended.
 +65 6479 9555
 surgery@anthonysiow.com